Difference Between a Referral and a Prior Authorization
Referrals clear specialist visits; prior authorizations clear specific procedures.
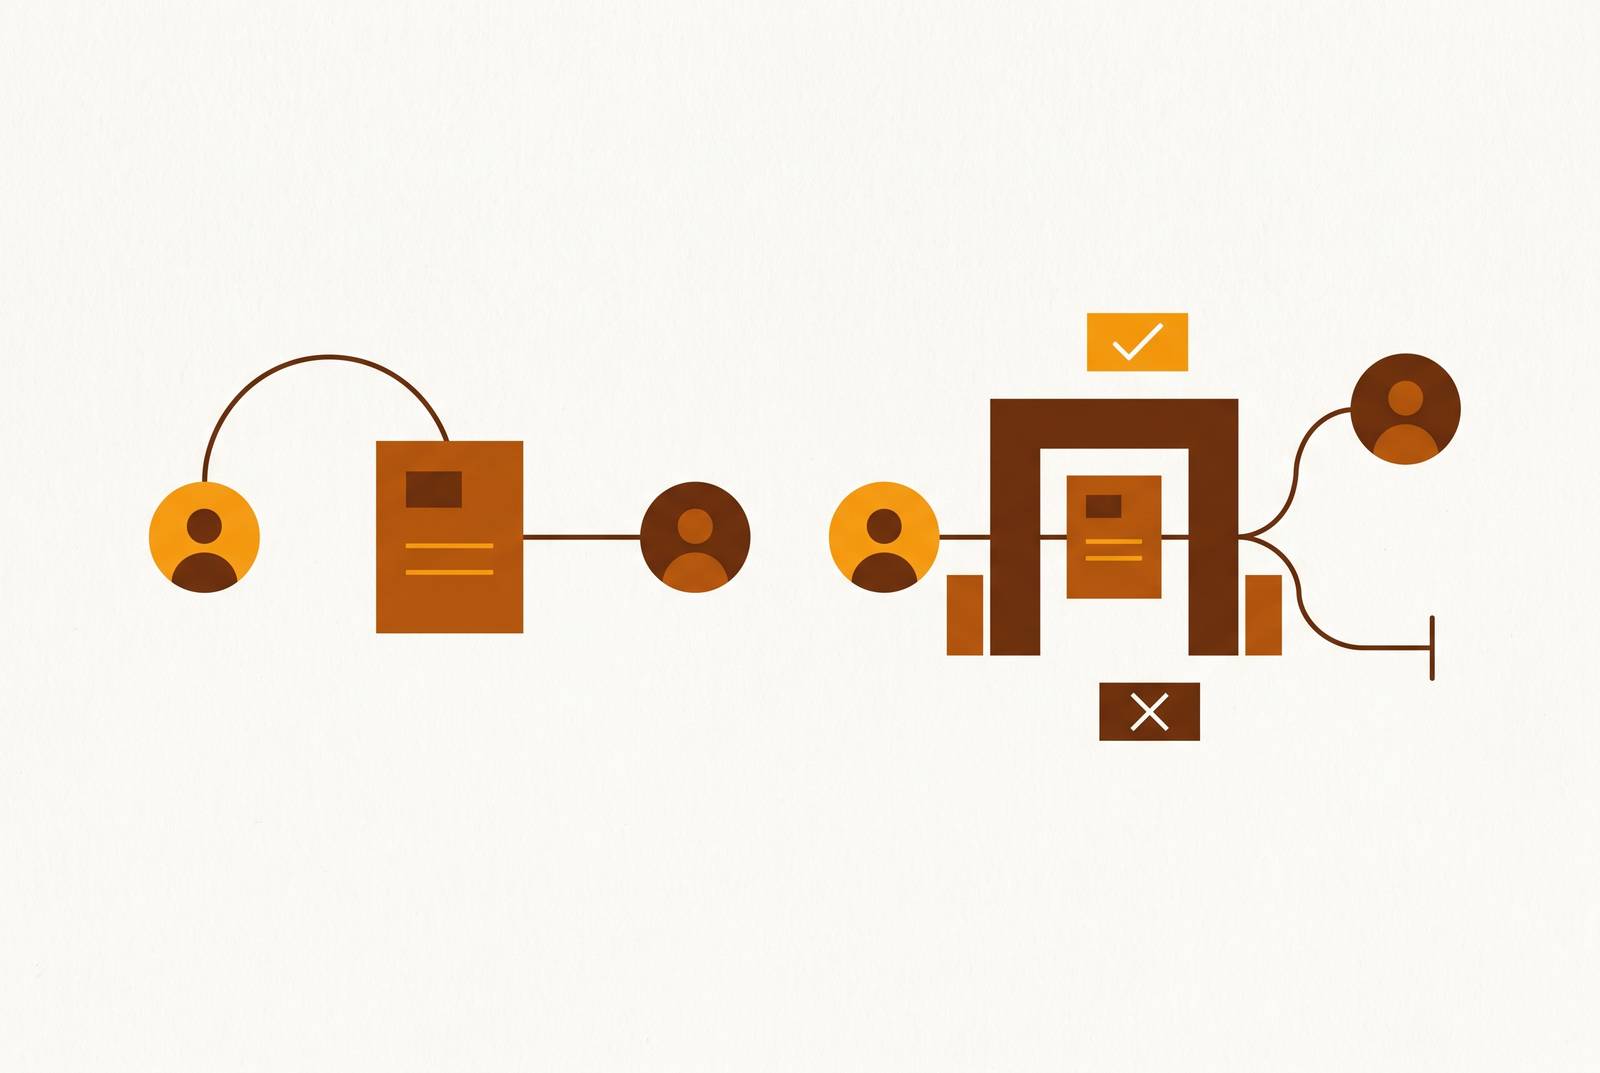
A referral and a prior authorization are two different instruments that happen to look alike at the front desk: both sit in front of a visit, and both can sink a claim if they're missing. A specialist visit can get denied even though the referral was on file, because the referral never covered the MRI the specialist ordered. It is the predictable result of treating two separate mechanisms as one clearance step.
Why Referrals and Prior Authorizations Are Routinely Confused
The confusion is structural. A referral and a prior authorization sit at different layers of the care and billing cycle: a referral is a clinical hand-off between providers, while a prior authorization is a payer's advance coverage decision. Those two layers don't announce themselves on a single intake record, so front-office staff, under time pressure and working from incomplete documentation, treat "the patient is cleared" as a single state rather than two separate conditions that each need their own proof. A valid referral to an orthopedic specialist does not satisfy the prior authorization that the plan requires before it will pay for the MRI that specialist orders. The referral and the authorization approve different things, at different points in the encounter, for different reasons, and nothing about a routine intake process forces that distinction into view.
Payer language makes the problem worse. Insurers use "precertification," "preauthorization," and "prior authorization" more or less interchangeably, and staff who hear a payer representative confirm any one of those terms often assume the other two are covered too. None of those three labels means the same thing as a referral, no matter how similar they sound over the phone or how often they appear on the same fax confirmation. A practice that absorbs this vocabulary without separating the underlying mechanisms is building a billing process on a misunderstanding that will become a denial.
What a Referral Is
A referral is a clinical instrument, not a payer decision. A treating provider, most often a primary care physician, documents that a patient should receive care from another provider, and that documentation is what the plan requires before it will recognize the specialist visit as covered. The action behind a referral originates with the provider, not the insurance company: the NAIC describes a referral as an order from a primary care provider to see a specialist or receive certain medical services.
A referral is narrow in scope and limited in time. It answers one question: may this patient see this specialist under the terms of the plan? It typically covers a specific specialty or a named provider, for a defined number of visits or a fixed window of time, and it says nothing at all about whether any particular procedure that specialist later recommends will be paid for. The referral is about the relationship between the patient and the specialist, not about any service performed during that relationship.
The referring physician's office initiates the referral, whether by logging into a payer portal or submitting a form directly to the specialist's office, so the action begins on the provider side of the transaction. Some plans will accept a verbal referral, but a written referral that is documented, logged, and attached to the correct patient record is the only version that protects a practice when a claim is reviewed. A referral clears the visit. It does not clear anything that happens during the visit.
What a Prior Authorization Is
Prior authorization is a coverage instrument issued by the health plan or its utilization-management delegate. It is the payer's advance determination that a specific service, item, or medication meets its coverage and medical-necessity criteria before that service is rendered. The NAIC defines prior authorization as approval from the health plan before receiving services, and that definition places the decision-making authority entirely on the payer's side of the table, in direct contrast to the provider-initiated referral.
Whether it's the specialist proposing surgery or the physician ordering advanced imaging, the rendering provider has to submit the authorization request along with clinical documentation that justifies medical necessity. The patient does not initiate this process and typically has no visibility into it until the appointment is scheduled or rescheduled. What gets approved is specific and tightly bound: particular procedure codes, approved providers, locations, dates of service, and authorized units or visits. A mismatch in any one of those fields at adjudication triggers an automated denial. The evidence of approval is an authorization number issued by the payer, and that number has to be captured, retained, and carried through to the claim or it does the practice no good.
Terminology adds a second trap here. Some payers call this precertification, others call it preauthorization, but both are labels for the same mechanism. Predetermination is a different animal entirely: a non-binding coverage estimate that does not constitute approval of anything. A prior authorization does not guarantee payment. Final reimbursement still depends on the patient's active coverage on the date of service, the plan's benefit structure, network participation, accurate coding, timely claim submission, and strict compliance with the terms of the authorization itself. A practice that treats an authorization number as a payment guarantee is setting itself up for a retrospective denial it won't see coming until the remittance advice arrives.
How Plan Design Determines Which Requirement Applies
Whether an encounter needs a referral, a prior authorization, both, or neither is set by the patient's specific plan at the time of service, not by any universal rule tied to a plan category. HMO plans are the primary home of the referral requirement: the plan routes specialist access through a gatekeeper PCP, and self-referred specialist care commonly isn't covered outside of an emergency. HMOs often layer prior authorization requirements on top of that referral requirement for higher-cost services, so if an HMO patient wants an MRI from a specialist, they may need both a referral and a separate authorization before the claim will pay.
PPO and EPO plans generally drop the referral requirement, letting a patient book a specialist directly, but they retain prior authorization requirements for imaging, surgeries, admissions, specialty drugs, and comparable high-cost services. This is where practices serving patients who move between plan types get caught: the assumption that a PPO's referral freedom also means authorization freedom is wrong, and the missed authorizations that follow from that assumption generate denials that have nothing to do with the quality of care delivered.
Even within a single insurer, the rules diverge by product. Medicare.gov states that Medicare Advantage HMO members generally need a specialist referral, with some exceptions, but its guidance on Medicare Advantage PPO plans says a specialist referral is not required. The same insurer brand can require opposite referral rules depending on which product the member actually holds. UnitedHealthcare's 2026 provider guide treats referral, advance notification, and prior authorization as three separate processes, and describes a uniform electronic PCP referral requirement for its Navigate, Navigate Balanced, and Navigate Plus products, while noting that Navigate Balanced and Navigate Plus allow additional network coverage, at a higher member cost-share, for services from a Navigate physician other than the member's PCP without a referral. A staff shortcut based only on the insurer's name loses all of that nuance. Plan type is a starting hypothesis about what an encounter will require, not a verification of it. The patient's actual plan document, confirmed at eligibility, is the only source a practice can safely act on.
Referral and Prior Authorization in a Single Encounter
A single specialist encounter can require both instruments, obtained in sequence and recorded separately, and having one in hand says nothing about whether the other has even been requested. Consider an HMO patient with knee pain who gets a referral from a primary care physician to see an orthopedic specialist. That referral satisfies the plan's rule that the patient be evaluated by a specialist, and it gets the patient into the exam room. If the orthopedist decides an MRI is needed, the referral does nothing for that next step. The specialist's billing team has to separately submit a prior authorization request to the payer before the imaging is performed, because the referral covered the evaluation and the authorization covers the procedure.
Three workflow failures account for most of the denials that follow from this sequence. The first is assuming a referral inherently includes authorization: a specialist's office receives the referral form, treats it as clearance for everything performed during the visit, and submits a claim for the MRI that gets denied because no separate authorization was ever sought. The second is relying on retroactive approval. Most commercial payers maintain that if an authorization is not active on the exact date of service, the claim is permanently denied, no matter how medically necessary the service turns out to be. The third is mismatched data at adjudication: an authorization obtained correctly but entered with a slightly different rendering provider NPI, an incorrect place-of-service code, or an unapproved diagnosis on the claim fails the automated match and gets denied, because payers run automated scrubbing algorithms that cross-reference incoming claims against the active authorizations on file.
Record-keeping discipline is what makes both instruments defensible when a claim is questioned. UnitedHealthcare's 2026 provider guide treats referral, advance notification, and prior authorization as separate processes, and a practice's internal records need to reflect that same separation, with distinct fields, distinct owners, and distinct statuses for each one. If a claim comes back denied on a technicality, an authorization number alone isn't enough to support a successful appeal; you need the approved service codes, the approved provider, the date range, and the authorized units attached to it.
Payer Behavior and 2026 Regulatory Changes
Payer requirements for referrals and prior authorizations are not fixed policy. They shift without notice, and the direction of movement in 2026 is toward more requirements, faster timelines, and higher denial rates on initial submissions. On the referral side, UnitedHealthcare's 2026 Medicare Advantage HMO and HMO-POS plans now require members to get a referral from their primary care provider before visiting certain specialists, with numerous specialty categories exempt, including oncology, mental health, OB/GYN, radiology, and podiatry among others. That gatekeeper requirement was previously absent for many of UnitedHealthcare's Medicare Advantage products. Practices that have treated their Medicare Advantage population as referral-free now face a new category of denial they haven't yet built a workflow to catch.
On the prior authorization side, the CMS Interoperability and Prior Authorization Final Rule, designated CMS-0057-F, introduces the most significant structural changes to the process in years. Payers covered by the rule must issue decisions within 7 calendar days for standard requests and within 72 hours for urgent requests. A practice that submits an incomplete request no longer has slack time to fix it before the clock runs out: the request has to be complete and accurate on the first attempt. Starting in 2026, payers covered by the rule must also provide a specific reason for every denied prior authorization, replacing the vague "does not meet criteria" language that has made appeals so difficult to construct, and giving practices something concrete to correct or contest. Covered payers must also publish aggregated prior authorization metrics annually, including approval rates, denial rates, and appeals outcomes, with the first reporting period covering calendar year 2025 and that data due by March 31, 2026. Beginning January 1, 2027, Medicare Advantage organizations, state Medicaid and CHIP programs and their managed care plans, and Qualified Health Plan issuers on the Federally Facilitated Exchanges must implement standardized electronic Prior Authorization systems under the same rule. Once the infrastructure is in place, practices that integrate with those APIs can get faster authorization turnaround and lower manual processing cost per transaction.
None of this reaches commercial employer-sponsored plans that are not sold on the ACA marketplace. For those plans, a different federal framework governs timelines on the self-funded employer side, while state law may govern fully insured commercial group plans that sit outside the exchanges. A practice with a mixed patient population, Medicare Advantage alongside commercial PPO alongside self-funded employer plans, is operating under three different regulatory regimes simultaneously, and a workflow built around only one of them will miss requirements that apply to the other two.
A verification workflow that treats referrals and prior authorizations as two separate checks, not one clearance step
The operational fix is to run two separate verification checks, one for referral requirements and one for authorization requirements, against the patient's actual plan at the time of service, and to record the outcome of each with its own source, its own status, and its own owner. Eligibility verification is the right moment to do both: confirming the patient's active plan, product, and network at intake reveals the referral requirement, which belongs to plan design, and the authorization requirement, which belongs to the specific service being ordered, before the appointment is even scheduled.
A single "approved" field in a patient's chart tells the billing team nothing useful. It doesn't say whether a referring clinician actually sent an order, whether the plan accepted that referral, whether an authorization was ever submitted, or whether the payer has made a decision on it. Each instrument needs its own entry: the referral record capturing the originating clinician, the destination, and the supporting document; the authorization record capturing the payer, the service, the reference number, the approved codes, the approved provider, the date range, and the authorized units. The handoff between the two has to be explicit too, a note that the referral document has been received sitting alongside the authorization's current status and its owner, never collapsed into a blanket "everything approved" that hides two open items behind one false signal of clearance.
Payer policy on both fronts changes often enough that annual review isn't sufficient. The services that require authorization and the plans that require referrals shift over time, so the only reliable verification source is the patient's active plan at the time of service, not last cycle's benefit check and not a standing assumption about what a particular insurer has always required. For a practice with staff turnover, a backed-up authorization queue, or a payer mix that keeps growing more complex, sustaining this two-track discipline in-house gets harder every quarter, and inconsistency raises the denial rate directly. A billing operation can absorb that burden on the practice's behalf if it holds payer-specific institutional memory, runs eligibility checks systematically, and maintains a dedicated authorization workflow. If a practice instead relies on individual staff members to hold all of that knowledge in their heads, it loses that knowledge the moment the employee leaves, and the denial rate rises until someone rebuilds what walked out the door.